Background: Fibromyalgia syndrome is a chronic pain disorder associated with autonomic dysfunction that may affect cardiac function. This study aimed to evaluate left ventricular diastolic function in fibromyalgia syndrome patients using echocardiography. Methods: A total of 140 participants were enrolled, including 70 patients with fibromyalgia syndrome and 70 age- and sex-matched healthy controls. All participants underwent conventional and tissue Doppler echocardiography. Diastolic parameters including peak early diastolic velocity, peak late diastolic velocity, ratio of peak early to peak late diastolic velocities, deceleration time, isovolumetric relaxation time, and ratio of early diastolic velocity to early diastolic myocardial velocity ratios were measured and compared between groups. Results: The two groups were comparable in terms of age, sex, body mass index, blood pressure, heart rate, and laboratory parameters. fibromyalgia syndrome patients had significantly larger left atrial dimensions (3.2±0.3 vs 3.0±0.1 cm, p=0.008), lower peak early diastolic velocity (0.72±0.07 vs 0.78±0.05 m/s, p=0.030), lower ratio of peak early to peak late diastolic velocities (1.14±0.15 vs 1.25±0.06, p=0.001), and prolonged isovolumetric relaxation time (99±8.5 vs 90±5.6 ms, p<0.001) compared to controls. Left ventricular ejection fraction and ratio of early diastolic velocity to early diastolic myocardial velocity ratios were similar between groups. Conclusion: Patients with fibromyalgia syndrome demonstrate subclinical left ventricular diastolic dysfunction as evidenced by impaired relaxation parameters on echocardiography. These findings suggest that cardiovascular evaluation should be considered in the routine assessment of fibromyalgia syndrome patients.
Fibromyalgia syndrome (FMS) is a chronic musculoskeletal disorder characterized by widespread pain, fatigue, sleep disturbances, and cognitive dysfunction. With a prevalence of approximately 2–8% in the general population, FMS predominantly affects women of working age and represents a significant burden on both individual quality of life and healthcare systems worldwide 1, 2.
Although FMS has traditionally been regarded as a functional disorder without identifiable organic pathology, accumulating evidence suggests that it may be associated with systemic dysregulation involving the autonomic nervous system, neuroendocrine pathways, and cardiovascular function 3, 4. Autonomic dysfunction, in particular, has been implicated in the pathophysiology of FMS, with studies demonstrating reduced heart rate variability and sympathovagal imbalance in affected individuals 5, 6. These autonomic disturbances may have downstream effects on cardiac function, particularly diastolic filling, which is highly sensitive to changes in sympathetic tone and myocardial relaxation.
Left ventricular diastolic dysfunction (LVDD) refers to impaired relaxation and filling of the left ventricle and is recognized as an early marker of subclinical cardiac involvement. It can be reliably assessed using conventional and tissue Doppler echocardiography, which provides non-invasive evaluation of parameters such as the E/A ratio, isovolumetric relaxation time (IVRT), deceleration time (DT), and E/E' ratio 7, 8. These indices have been used to detect early cardiac changes in various systemic and inflammatory conditions before the onset of overt heart failure.
Despite the growing interest in cardiovascular comorbidities in FMS, data on left ventricular diastolic function in this population remain limited and inconsistent. To our knowledge, few studies have systematically evaluated diastolic parameters using comprehensive echocardiographic assessment in FMS patients compared to healthy controls matched for age, sex, and metabolic risk factors.
Therefore, the aim of this study was to evaluate left ventricular diastolic function in patients with FMS using conventional and tissue Doppler echocardiography and to compare these findings with those of age- and sex-matched healthy controls.
Study Design and Participants
This prospective, cross-sectional study was conducted at the Niğde Ömer Halisdemir University Faculty of Medicine. The study protocol was approved by the local Non-Interventional Clinical Research Ethics Committee (Approval No: 2024/46), and written informed consent was obtained from all participants. A total of 140 individuals were enrolled, comprising 70 patients diagnosed with fibromyalgia syndrome (FMS group) and 70 age- and sex-matched healthy volunteers (control group). FMS diagnosis was established according to the 2010 American College of Rheumatology (ACR) diagnostic criteria, incorporating the widespread pain index (WPI) and symptom severity scale (SSS) scores 9. Sample size was determined via power analysis using G*Power software (version 3.1.9.4). Based on an alpha level of 0.05, a power (1-β) of 0.80, and an expected effect size of 0.65 for the primary outcome (intergroup E/A ratio difference) derived from pilot data, a minimum of 62 participants per group was required. To account for potential dropouts or non-evaluable echocardiographic data, the final cohort was increased to 70 participants per group (N=140).
Inclusion and Exclusion Criteria
Patients aged 18–65 years with a confirmed diagnosis of FMS were included. Exclusion criteria for both groups included known coronary artery disease, heart failure, valvular heart disease, arrhythmia, diabetes mellitus, renal or hepatic insufficiency, thyroid dysfunction, and use of medications known to affect cardiac function. Individuals with a BMI >35 kg/m² or uncontrolled hypertension were also excluded.
Clinical and Laboratory Assessment
Demographic data including age, sex, body mass index (BMI), systolic blood pressure (SBP), diastolic blood pressure (DBP), and heart rate were recorded for all participants. Fasting venous blood samples were obtained for measurement of fasting glucose, total cholesterol, LDL cholesterol, HDL cholesterol, triglycerides, and thyroid-stimulating hormone (TSH).
Echocardiographic Evaluation
All participants underwent transthoracic echocardiography performed by an experienced cardiologist blinded to group allocation, using EPIQ 7 Premium ultrasound system. Left ventricular ejection fraction (LVEF) was calculated using the modified Simpson's biplane method. Left ventricular end-diastolic dimension (LVEDD), end-systolic dimension (LVESD), interventricular septum (IVS) thickness, posterior wall (PW) thickness, and left atrial (LA) dimension were measured in M-mode and two-dimensional views according to current guidelines 10.
Diastolic function was assessed using pulsed-wave Doppler of the mitral inflow, measuring peak early (E) and late (A) diastolic velocities, E/A ratio, deceleration time (DT), and isovolumetric relaxation time (IVRT). Tissue Doppler imaging (TDI) was used to measure early diastolic myocardial velocities at the lateral (E' lateral) and septal (E' septal) mitral annulus. The E/E' ratio was calculated as a surrogate of left ventricular filling pressure 7.
Statistical Analysis
Statistical analyses were performed using SPSS version 25.0 (IBM Corp., Armonk, NY, USA). Continuous variables were expressed as mean ± standard deviation (SD) or median (interquartile range) depending on normality, assessed by the Kolmogorov–Smirnov test. Comparisons between groups were made using the independent samples t-test or Mann–Whitney U test as appropriate. Categorical variables were compared using the chi-square test. A p-value of <0.05 was considered statistically significant.
Clinical and Laboratory Characteristics
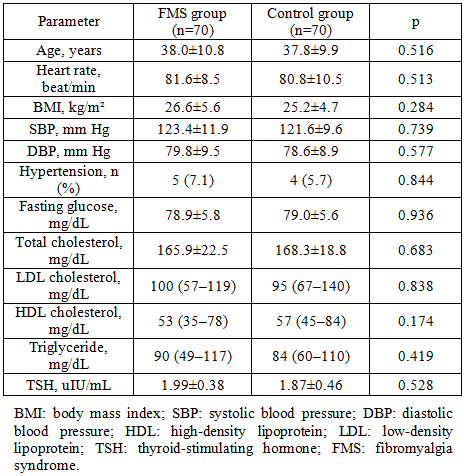
The FMS and control groups were well-matched in terms of baseline characteristics. Mean age was 38.0±10.8 years in the FMS group and 37.8±9.9 years in the control group (p=0.516). Heart rate, BMI, systolic and diastolic blood pressure were similar between groups (all p>0.05). The prevalence of hypertension was comparable (7.1% vs 5.7%, p=0.844). Laboratory parameters including fasting glucose, total cholesterol, LDL cholesterol, HDL cholesterol, triglycerides, and TSH did not differ significantly between the two groups (all p>0.05). These findings are summarized in Table 1.
Echocardiographic Parameters
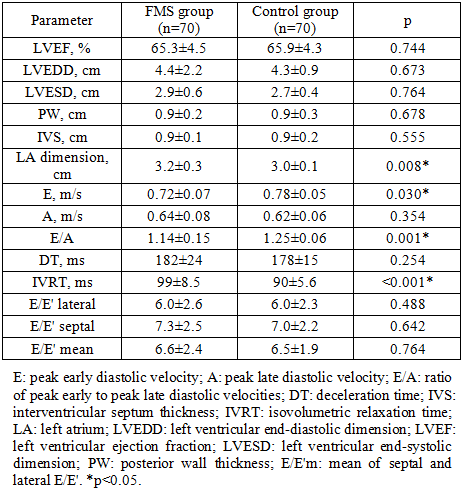
Left ventricular systolic function was preserved and similar in both groups, with mean LVEF of 65.3±4.5% in the FMS group and 65.9±4.3% in the control group (p=0.744). Structural parameters including LVEDD, LVESD, IVS, and PW thickness were also comparable between groups (all p>0.05).
However, significant differences were observed in diastolic function parameters. LA dimension was significantly larger in the FMS group compared to controls (3.2±0.3 vs 3.0±0.1 cm, p=0.008). Peak early diastolic velocity (E) was significantly lower in FMS patients (0.72±0.07 vs 0.78±0.05 m/s, p=0.030). The E/A ratio was significantly reduced in the FMS group (1.14±0.15 vs 1.25±0.06, p=0.001), and IVRT was significantly prolonged (99±8.5 vs 90±5.6 ms, p<0.001). Deceleration time did not differ significantly between groups (182±24 vs 178±15 ms, p=0.254). E/E' lateral, E/E' septal, and mean E/E' ratios were similar in both groups (all p>0.05). These results are presented in Table 2.
In this study, we evaluated left ventricular diastolic function in patients with FMS using conventional and tissue Doppler echocardiography. Our main findings were that FMS patients had significantly impaired diastolic relaxation parameters — including reduced E velocity, lower E/A ratio, prolonged IVRT, and larger LA dimensions — compared to age- and sex-matched healthy controls and comparable filling pressure indices (E/E' ratios).
The pathophysiological basis for diastolic dysfunction in FMS likely involves autonomic nervous system dysregulation. Chronic sympathetic overactivation and parasympathetic withdrawal, well-documented in FMS, can impair myocardial relaxation by altering calcium handling in cardiomyocytes and increasing myocardial stiffness 3, 5. Martínez-Lavín et al. demonstrated significant sympathetic hyperactivity in FMS patients through heart rate variability analysis, which may directly affect ventricular relaxation kinetics 4. Our findings of prolonged IVRT and reduced E velocity are consistent with grade I diastolic dysfunction (impaired relaxation pattern), suggesting that autonomic imbalance in FMS translates into measurable subclinical cardiac changes.
The significantly enlarged LA dimension observed in FMS patients in our study is noteworthy. Left atrial enlargement is a well-established marker of chronic elevation of left ventricular filling pressures and diastolic dysfunction 11. Although E/E' ratios — which reflect filling pressures more acutely — were normal and similar between groups, the LA enlargement may reflect a cumulative effect of chronically impaired relaxation over time. This finding underscores the importance of LA dimension as a complementary marker in the echocardiographic assessment of diastolic function.
Our results are in line with previous studies suggesting subclinical cardiac involvement in FMS. Akkaya et al. reported impaired left ventricular diastolic function in FMS patients, with prolonged IVRT and reduced E/A ratio, findings that closely mirror our own 12. Similarly, Sert et al. demonstrated diastolic dysfunction in FMS patients using tissue Doppler imaging, further supporting the notion that FMS is not purely a musculoskeletal condition but may have systemic cardiovascular implications 13.
The preservation of systolic function (LVEF) and E/E' ratios in our cohort suggests that the cardiac involvement in FMS is in an early, subclinical stage. This is consistent with the concept that diastolic dysfunction precedes systolic dysfunction in most cardiac conditions and may represent a window of opportunity for early intervention 7. Identifying patients at risk for progressive cardiac dysfunction through routine echocardiographic screening may be clinically relevant in the long-term management of FMS.
Chronic pain, psychological stress, and poor sleep quality — hallmarks of FMS — may also contribute to cardiac dysfunction through neurohumoral mechanisms, including activation of the renin-angiotensin-aldosterone system and elevated inflammatory cytokines 14. These factors may promote myocardial fibrosis and impaired relaxation independently of traditional cardiovascular risk factors, which were well-controlled in our study population.
This study has several limitations. First, its cross-sectional design precludes causal inference. Second, we did not assess disease severity scores (e.g., Fibromyalgia Impact Questionnaire) or pain duration, which may correlate with the degree of diastolic dysfunction. Third, the relatively young and predominantly female study population may limit generalizability. Future longitudinal studies with larger cohorts and detailed clinical characterization are warranted to confirm these findings and explore the clinical implications of diastolic dysfunction in FMS.
Patients with fibromyalgia syndrome demonstrate subclinical left ventricular diastolic dysfunction, characterized by impaired relaxation parameters including reduced E velocity, lower E/A ratio, prolonged IVRT, and enlarged left atrial dimensions. These findings suggest that cardiovascular evaluation, including echocardiographic assessment of diastolic function, should be considered as part of the comprehensive management of FMS patients. Further prospective studies are needed to elucidate the clinical significance and long-term cardiovascular implications of these findings.
Ethics Approval and Consent to Participate
This study was approved by Niğde Ömer Halisdemir University Faculty of Medicine, Non-Interventional Clinical Research Ethics Committee (Approval No: 2024/46). All procedures were conducted in accordance with the 1975 Declaration of Helsinki, updated in 2013. Written informed consent was obtained from all participants included in the study.
Not applicable.
The datasets used and/or analysed during the current study are available from the corresponding author on reasonable request.
The authors declare that they have no competing interests.
There was no external funding source for this study.
HA conceived and designed the study, collected and acquired the data, performed statistical analysis, interpreted the results, drafted the manuscript, and critically revised it for important intellectual content. HA read and approved the final manuscript.
Not applicable.
| [1] | Kocyigit BF, Akyol A. Fibromyalgia syndrome: epidemiology, diagnosis and treatment. Reumatologia. 2022; 60(6): 413–421. | ||
| In article | View Article PubMed | ||
| [2] | Neumann L, Buskila D. Epidemiology of fibromyalgia. Curr Pain Headache Rep. 2003; 7(5): 362–368. | ||
| In article | View Article PubMed | ||
| [3] | Siracusa R, Paola RD, Cuzzocrea S, Impellizzeri D. Fibromyalgia: pathogenesis, mechanisms, diagnosis and treatment options update. Int J Mol Sci. 2021; 22(8): 3891. | ||
| In article | View Article PubMed | ||
| [4] | Martínez-Lavín M, Hermosillo AG, Rosas M, Soto ME. Circadian studies of autonomic nervous balance in patients with fibromyalgia: a heart rate variability analysis. Arthritis Rheum. 1998; 41(11): 1966–1971. | ||
| In article | View Article PubMed | ||
| [5] | Cohen H, Neumann L, Shore M, Amir M, Cassuto Y, Buskila D. Autonomic dysfunction in patients with fibromyalgia: application of power spectral analysis of heart rate variability. Semin Arthritis Rheum. 2000; 29(4): 217–227. | ||
| In article | View Article PubMed | ||
| [6] | Kang JH, Kim JK, Hong SH, Lee CH, Choi BY. Heart rate variability for quantification of autonomic dysfunction in fibromyalgia. Ann Rehabil Med. 2016; 40(2): 301–309. | ||
| In article | View Article PubMed | ||
| [7] | Nagueh SF, Smiseth OA, Appleton CP, et al. Recommendations for the evaluation of left ventricular diastolic function by echocardiography: an update from the American Society of Echocardiography and the European Association of Cardiovascular Imaging. J Am Soc Echocardiogr. 2016; 29(4): 277–314. | ||
| In article | View Article PubMed | ||
| [8] | Bruch C, Marin D, Kuntz S, et al. Analysis of mitral annulus excursion with tissue Doppler echocardiography: noninvasive assessment of left ventricular diastolic dysfunction. Z Kardiol. 1999; 88(5): 353–362. | ||
| In article | View Article PubMed | ||
| [9] | Wolfe F, Clauw DJ, Fitzcharles MA, et al. The American College of Rheumatology preliminary diagnostic criteria for fibromyalgia and measurement of symptom severity. Arthritis Care Res (Hoboken). 2010; 62(5): 600–610. | ||
| In article | View Article PubMed | ||
| [10] | Lang RM, Badano LP, Mor-Avi V, et al. Recommendations for cardiac chamber quantification by echocardiography in adults: an update from the American Society of Echocardiography and the European Association of Cardiovascular Imaging. J Am Soc Echocardiogr. 2015; 28(1): 1–39.e14. | ||
| In article | View Article PubMed | ||
| [11] | Tsang TS, Barnes ME, Gersh BJ, Bailey KR, Seward JB. Left atrial volume as a morphophysiologic expression of left ventricular diastolic dysfunction and relation to cardiovascular risk burden. Am J Cardiol. 2002; 90(12): 1284–1289. | ||
| In article | View Article PubMed | ||
| [12] | Akkaya M, Nacar AB, Arlı H, et al. Evaluation of left ventricular diastolic functions in patients with fibromyalgia syndrome. Eur J Rheumatol. 2014; 1(3): 95–99. | ||
| In article | |||
| [13] | Sert A, Aypar E, Odabas AR, et al. Left ventricular diastolic dysfunction in fibromyalgia patients. Echocardiography. 2013; 30(3): 280–286. | ||
| In article | |||
| [14] | Staud R. Autonomic dysfunction in fibromyalgia syndrome: postural orthostatic tachycardia. Curr Rheumatol Rep. 2008; 10(6): 463–466. | ||
| In article | View Article PubMed | ||
Published with license by Science and Education Publishing, Copyright © 2026 Hasan Akkaya
 This work is licensed under a Creative Commons Attribution 4.0 International License. To view a copy of this license, visit
http://creativecommons.org/licenses/by/4.0/
| [1] | Kocyigit BF, Akyol A. Fibromyalgia syndrome: epidemiology, diagnosis and treatment. Reumatologia. 2022; 60(6): 413–421. | ||
| In article | View Article PubMed | ||
| [2] | Neumann L, Buskila D. Epidemiology of fibromyalgia. Curr Pain Headache Rep. 2003; 7(5): 362–368. | ||
| In article | View Article PubMed | ||
| [3] | Siracusa R, Paola RD, Cuzzocrea S, Impellizzeri D. Fibromyalgia: pathogenesis, mechanisms, diagnosis and treatment options update. Int J Mol Sci. 2021; 22(8): 3891. | ||
| In article | View Article PubMed | ||
| [4] | Martínez-Lavín M, Hermosillo AG, Rosas M, Soto ME. Circadian studies of autonomic nervous balance in patients with fibromyalgia: a heart rate variability analysis. Arthritis Rheum. 1998; 41(11): 1966–1971. | ||
| In article | View Article PubMed | ||
| [5] | Cohen H, Neumann L, Shore M, Amir M, Cassuto Y, Buskila D. Autonomic dysfunction in patients with fibromyalgia: application of power spectral analysis of heart rate variability. Semin Arthritis Rheum. 2000; 29(4): 217–227. | ||
| In article | View Article PubMed | ||
| [6] | Kang JH, Kim JK, Hong SH, Lee CH, Choi BY. Heart rate variability for quantification of autonomic dysfunction in fibromyalgia. Ann Rehabil Med. 2016; 40(2): 301–309. | ||
| In article | View Article PubMed | ||
| [7] | Nagueh SF, Smiseth OA, Appleton CP, et al. Recommendations for the evaluation of left ventricular diastolic function by echocardiography: an update from the American Society of Echocardiography and the European Association of Cardiovascular Imaging. J Am Soc Echocardiogr. 2016; 29(4): 277–314. | ||
| In article | View Article PubMed | ||
| [8] | Bruch C, Marin D, Kuntz S, et al. Analysis of mitral annulus excursion with tissue Doppler echocardiography: noninvasive assessment of left ventricular diastolic dysfunction. Z Kardiol. 1999; 88(5): 353–362. | ||
| In article | View Article PubMed | ||
| [9] | Wolfe F, Clauw DJ, Fitzcharles MA, et al. The American College of Rheumatology preliminary diagnostic criteria for fibromyalgia and measurement of symptom severity. Arthritis Care Res (Hoboken). 2010; 62(5): 600–610. | ||
| In article | View Article PubMed | ||
| [10] | Lang RM, Badano LP, Mor-Avi V, et al. Recommendations for cardiac chamber quantification by echocardiography in adults: an update from the American Society of Echocardiography and the European Association of Cardiovascular Imaging. J Am Soc Echocardiogr. 2015; 28(1): 1–39.e14. | ||
| In article | View Article PubMed | ||
| [11] | Tsang TS, Barnes ME, Gersh BJ, Bailey KR, Seward JB. Left atrial volume as a morphophysiologic expression of left ventricular diastolic dysfunction and relation to cardiovascular risk burden. Am J Cardiol. 2002; 90(12): 1284–1289. | ||
| In article | View Article PubMed | ||
| [12] | Akkaya M, Nacar AB, Arlı H, et al. Evaluation of left ventricular diastolic functions in patients with fibromyalgia syndrome. Eur J Rheumatol. 2014; 1(3): 95–99. | ||
| In article | |||
| [13] | Sert A, Aypar E, Odabas AR, et al. Left ventricular diastolic dysfunction in fibromyalgia patients. Echocardiography. 2013; 30(3): 280–286. | ||
| In article | |||
| [14] | Staud R. Autonomic dysfunction in fibromyalgia syndrome: postural orthostatic tachycardia. Curr Rheumatol Rep. 2008; 10(6): 463–466. | ||
| In article | View Article PubMed | ||